Published in PLOS One on 2026-09-15, this study is presented as an attributed evidence briefing. The excerpts below are the original researchers’ words, reproduced under their Creative Commons Attribution licence. Health Signal has selected the abstract and, where needed, opening background paragraphs; the complete methods, results, limitations and references remain in the linked paper.
Original study title: Association between anthropometric criteria and body composition among children aged 6–59 months with uncomplicated severe acute malnutrition: A prospective cohort study from South Sudan
Original authors: Gabriele Rossi, Rachel M. Creighton, Patricia Ayebazibwe, Santo Garang, Mohammed Kamruzzaman, Taesung Park, Namseon Beck, Wendy Dyment
Source: PLOS One • DOI 10.1371/journal.pone.0356530
Read the complete primary study ↗ · Creative Commons Attribution licence
From the researchers
Abstract
Severe acute malnutrition (SAM) is diagnosed based on bilateral edema, mid‑upper arm circumference (MUAC), and/or weight‑for‑height z‑score (WHZ). These criteria do not fully overlap and may identify children with distinct biological and clinical profiles. Understanding how children with SAM identified by different criteria differ in body composition during outpatient therapeutic program (OTP) treatment may help inform treatment and post‑discharge practices.
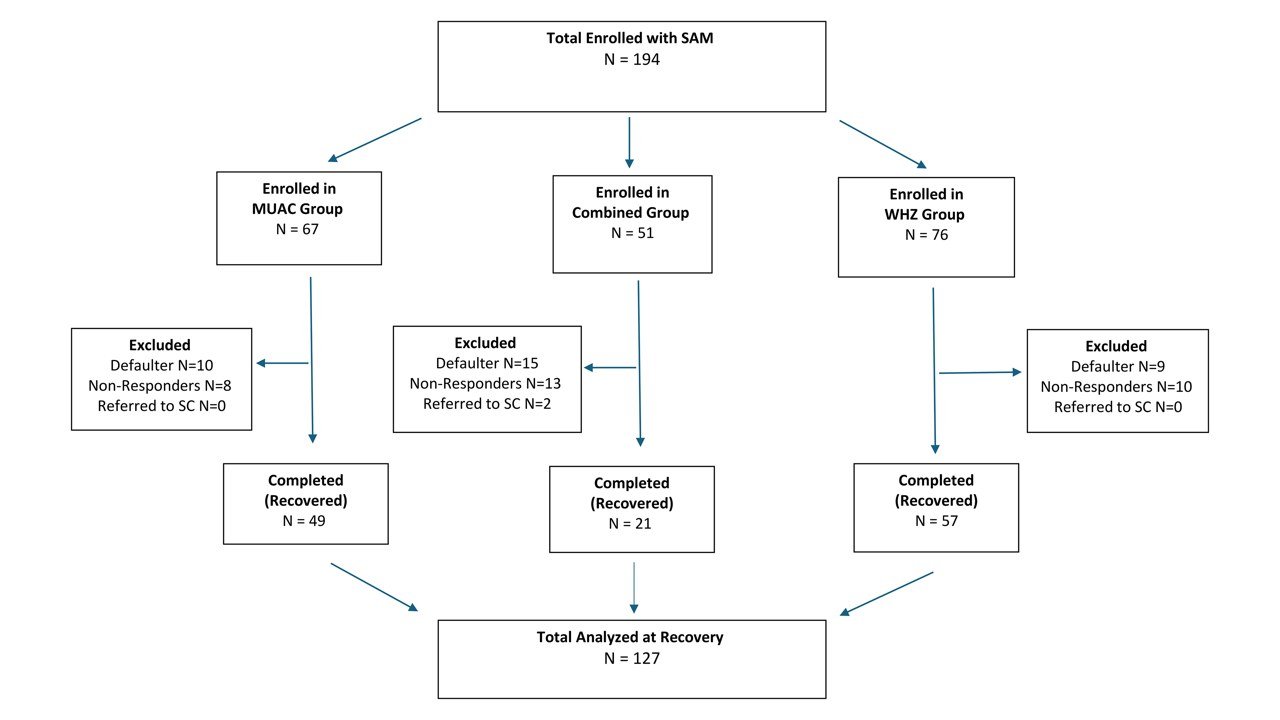
We conducted a prospective cohort study of children aged 6–59 months with uncomplicated SAM admitted by MUAC only (MUAC group), WHZ only (WHZ group), or combined MUAC and WHZ criteria (Combined group) in Aweil Centre, South Sudan. Anthropometry, triceps skinfold thickness, and bioelectrical impedance analysis were collected at admission (n = 194) and discharge (n = 127). Fat mass (FM), fat‑free mass (FFM), fat mass index (FMI), fat‑free mass index (FFMI), total body water percentage (TBW), and phase angle (PhA) were assessed. Between‑group differences and within‑child changes were analyzed using linear mixed effects models adjusted for age and sex.
At admission, children in the MUAC and Combined groups were younger and more stunted, with the Combined group showing the most severe deficits across anthropometry, FMI, and PhA. During treatment, the WHZ group exhibited the fastest recovery, with predominantly FFM accretion (82% of weight gain) and the largest increases in FFMI. In contrast, the MUAC group accumulated mainly FM (78% of weight gain) with minimal FFM gain and a decline in PhA, while the Combined group showed mixed FM and FFM recovery patterns.
Children admitted for outpatient SAM treatment by MUAC, WHZ, or combined criteria appeared to follow different recovery trajectories despite meeting standard anthropometric discharge thresholds. Body‑composition and impedance indicators suggested heterogeneity in tissue gain patterns and vulnerability profiles across admission groups, particularly in the MUAC and Combined groups. While exploratory, these findings suggest that anthropometric recovery alone may not uniformly capture the full recovery pattern across SAM admission groups, warranting the need for longitudinal studies evaluating whether body-composition differences at discharge predict subsequent clinical outcomes and post-discharge vulnerability.
Introduction
In 2024, an estimated 6.6% of children under five globally were affected by acute malnutrition and 1.9% by severe acute malnutrition (SAM), corresponding to 42.8 million and 12.2 million children, respectively, according to the United Nations Children’s Fund (UNICEF) [1]. Current World Health Organization (WHO) guidelines promote a public health approach emphasizing high program coverage, early identification, and differentiated care. Children with uncomplicated SAM—defined by anthropometric deficits without danger signs and/or bilateral edema—are treated as outpatients in the Outpatient Therapeutic Program (OTP) with ready‑to‑use therapeutic food (RUTF), while medically complicated cases require inpatient stabilization care. These pathways, introduced in 2013 and updated in 2023, emphasize prevention, early detection, outpatient management, and continuity of care following discharge [2].
Reading this evidence
Use the full paper to check the study design, participant selection, comparator and outcome definitions before drawing a practical conclusion. An association does not by itself show cause and effect. A reported performance measure needs its denominator and uncertainty. A finding from a particular facility, sample or time period should retain that scope when it is discussed elsewhere.
This briefing makes the source accessible within the wider research & evidence desk. It does not assess an individual patient or certify a product. When considering relevance to another health system, examine the original authors’ account of context and limitations, then seek local implementation evidence. The related reporting below provides other studies to read alongside this one; it is a topic connection, rather than a claim that their results are directly comparable.
© 2026 Gabriele Rossi, Rachel M. Creighton, Patricia Ayebazibwe, Santo Garang, Mohammed Kamruzzaman, Taesung Park, Namseon Beck, Wendy Dyment. Excerpts reproduced under CC BY. Selection, formatting and contextual notes by Health Signal. The researchers are the authors of the source study, not members of Health Signal’s staff.
Explore connected evidence
- Evidence brief: Body composition of children born HIV-exposed uninfected in rural Zimbabwe
- Evidence brief: Time to recovery and its predictors among children aged 6 to 59 months with uncomplicated severe acute malnutrition treated in outpatient therapeutic programs in Adet Woreda, Central Zone of Tigray, Northern Ethiopia: A retrospective cohort study
- Evidence brief: Prevalence, diagnostic methods, and clinical outcomes of wasting among paediatric cancer patients in Africa: A systematic review and meta-analysis