Published in PLOS One on 2026-09-09, this study is presented as an attributed evidence briefing. The excerpts below are the original researchers’ words, reproduced under their Creative Commons Attribution licence. Health Signal has selected the abstract and, where needed, opening background paragraphs; the complete methods, results, limitations and references remain in the linked paper.
Original authors: Kofi Effah, Ethel Tekpor, Maxwell Afetor, Joseph Emmanuel Amuah, Comfort Mawusi Wormenor, Annita Edinam Dugbazah, Stephen Danyo, Seyram Kemawor, Edna Sesenu, Christopher Nyamekye, Emmanuel Timmy Donkoh, Chrysantus Kubio, Kofi Adum-Attah
Source: PLOS One • DOI 10.1371/journal.pone.0345847
Read the complete primary study ↗ · Creative Commons Attribution licence
From the researchers
Abstract
Visual Inspection with Acetic acid (VIA) is widely used for detecting cervical (pre)cancer in resource-limited settings due to its simplicity and cost-effectiveness. However, the finding of cervical leukoplakia, poses diagnostic challenges.
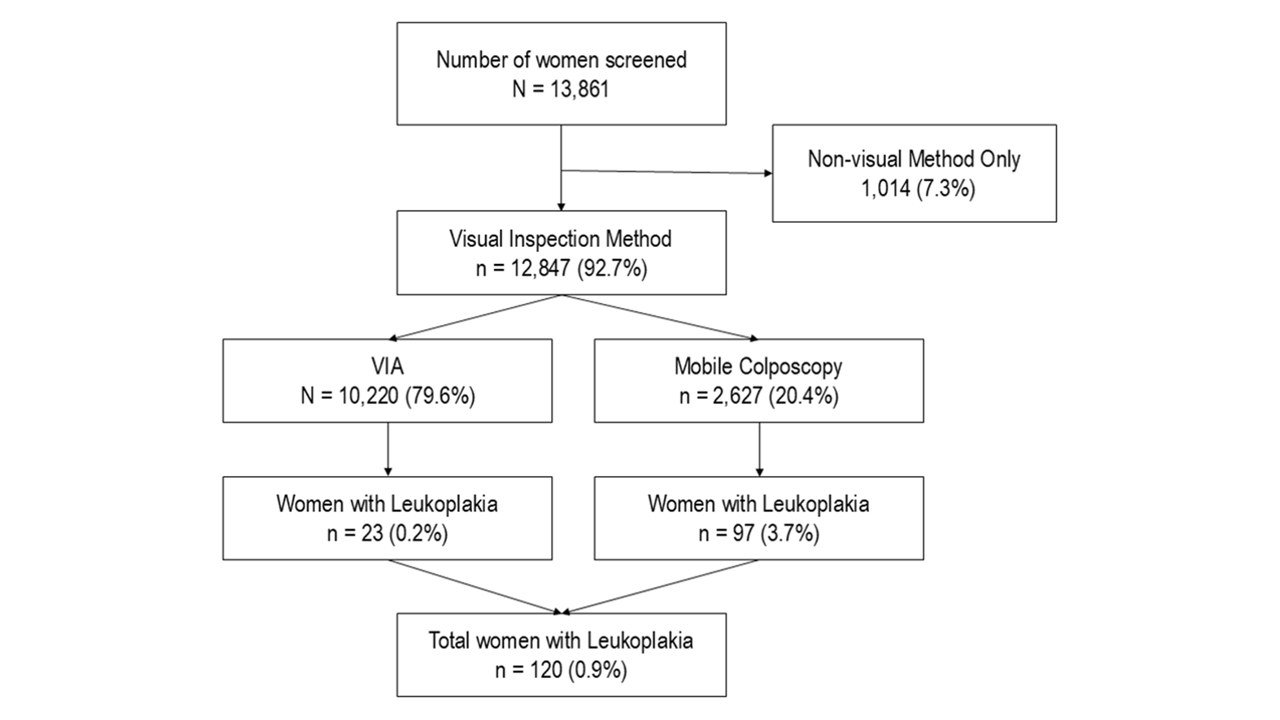
This retrospective observational study evaluated the prevalence, associated risk factors, and referral outcomes of cervical leukoplakia among 13,861 women previously screened for cervical cancer in Ghana between June 2016 and May 2024. Screening approaches included VIA alone, mobile colposcopy alone, or VIA/mobile colposcopy combined with other tests (HPV DNA testing and/or cytology).
Among 120 women (0.9%) with leukoplakia, 112 (93.3%) did not have acetowhitening on VIA/mobile colposcopy, and 21 (17.5%) received LEEP. The histopathology results ranged from no Cervical Intraepithelial Neoplasia (CIN) (15) to CIN I (2), CIN II (1), and CIN III (3). High-risk HPV positivity (aOR: 30.27; 95% CI: 3.56–257.37) and HIV infection (aOR: 8.27; 95% CI: 1.18–57.69) were associated with higher odds of leukoplakia in VIA-screened women.
Leukoplakia can be clinically important without coexistence with acetowhitening. The association of leukoplakia with hrHPV and HIV, coupled with a high referral default and logistical barriers to biopsy and histopathology, calls for simplified management protocols and point-of-care triage tools for cervical screening in low-resource settings.
Introduction
Cervical cancer remains a major contributor to cancer-related mortality in women worldwide, particularly in low- and middle-income countries (LMICs) [1]. In Ghana, it is the second most prevalent malignancy among women, with an annual incidence of 2,797 cases and 1,699 associated fatalities [1]. The disproportionate mortality stems from systemic challenges that delay recognition of precursor lesions and limit access to prompt treatment, both essential for attaining disease elimination targets [2–5]. Timely identification of cervical precancerous lesions holds promise for reducing the risk of cancer. In low-resource settings, cytology-based screening faces significant obstacles, including shortages of trained personnel, inadequate infrastructure, and high costs [6]. As a result, visual inspection methods are a pragmatic choice for expanding access to screening services because of their affordability and accessibility.
Leukoplakia, a non-scrapable white lesion visible on the cervix before acetic acid application, is a common finding during Visual Inspection with Acetic acid (VIA) or colposcopy [7,8]. Unlike acetowhite lesions, leukoplakia is discernible without acetic acid and may indicate underlying high-grade lesions or invasive pathology [9]. It may result from hyperkeratosis, chronic inflammation, or HPV-related epithelial changes. However, its opaque appearance can obscure underlying high-grade Cervical Intraepithelial Neoplasia (CIN2/3) or invasive carcinoma and is associated with a higher likelihood of concealing severe dysplasia or malignancy on biopsy [10,11]. This diagnostic challenge underscores the importance of histological evaluation in cases of leukoplakia to rule out serious pathology, particularly in settings where advanced imaging or molecular testing is limited [11–13]. The clinical significance of leukoplakia has been well-documented in other mucosal tissues; however, its diagnostic importance in cervical screening is insufficiently explored [9]. Research indicates varying relationships between leukoplakia and cervical (pre)cancer or cancer, shaped by population-specific factors, including HPV genotype distribution, immune status, and healthcare access [10,13–15]. These inconsistencies highlight the need for further evidence to clarify the interplay between leukoplakia and established predictors of cervical intraepithelial lesions.
Reading this evidence
Use the full paper to check the study design, participant selection, comparator and outcome definitions before drawing a practical conclusion. An association does not by itself show cause and effect. A reported performance measure needs its denominator and uncertainty. A finding from a particular facility, sample or time period should retain that scope when it is discussed elsewhere.
This briefing makes the source accessible within the wider technology & industry desk. It does not assess an individual patient or certify a product. When considering relevance to another health system, examine the original authors’ account of context and limitations, then seek local implementation evidence. The related reporting below provides other studies to read alongside this one; it is a topic connection, rather than a claim that their results are directly comparable.
© 2026 Kofi Effah, Ethel Tekpor, Maxwell Afetor, Joseph Emmanuel Amuah, Comfort Mawusi Wormenor, Annita Edinam Dugbazah, Stephen Danyo, Seyram Kemawor, Edna Sesenu, Christopher Nyamekye, Emmanuel Timmy Donkoh, Chrysantus Kubio, Kofi Adum-Attah. Excerpts reproduced under CC BY. Selection, formatting and contextual notes by Health Signal. The researchers are the authors of the source study, not members of Health Signal’s staff.
Explore connected evidence
- Evidence brief: A collaborative cervical precancer screening strategy with concurrent HPV genotyping and visual inspection using alumni of a training centre across Ghana: The Rotary ‘Protect Your Pearl’ initiative
- Evidence brief: Genotype distribution of high-risk and potential high-risk HPV types among women in different screening and clinic settings in Ghana and Kenya
- Evidence brief: Impact of menopausal status on human papillomavirus detection and cervical neoplasia in middle-aged Senegalese women