Published in PLOS One on 2026-08-28, this study is presented as an attributed evidence briefing. The excerpts below are the original researchers’ words, reproduced under their Creative Commons Attribution licence. Health Signal has selected the abstract and, where needed, opening background paragraphs; the complete methods, results, limitations and references remain in the linked paper.
Original authors: Eliza Mari Kwesi-Maliepaard, Judith A. Osea-Larbi, Celestine K. Nyamari, Yakubu Alhassan, Adelaide K. Sromani, Vera M. Kotey, Stephanie Darko, Randy Tackie, Ruth Kiome, Aisha M. Mohammed, Erica Buadii, Emmanuel K. Quaye, Harry Akligoh, Barikisu A. Ibrahim, Patricia Kaba, Susan Florence Amoako, Esmy Kotey, Seth Agyemang, Joyce M. Ngoi, Lily Paemka, Kwaku Darkwa, Thywill Degley, Nathan Edward Siebu, Charles Ochieng’ Olwal, Collins M. Morang’a, Aida Manu, David Hutchful, Emmanuella Amoako, Frank G. Onyambu, Yaw Bediako
Source: PLOS One • DOI 10.1371/journal.pone.0355868
Read the complete primary study ↗ · Creative Commons Attribution licence
From the researchers
Abstract
The burden of cervical cancer is highest in Africa. Human papillomavirus (HPV) infection is the major cause of cervical cancer. There are over 200 different HPV genotypes, with 15 considered (potential) high-risk genotypes for developing cancer. Due to a lack of systematic screening programs in most African countries, there is limited data available on the most prevalent HPV genotypes in the population. This study aimed to assess the prevalence and distribution of HPV genotypes in cohorts in Ghana and Kenya.
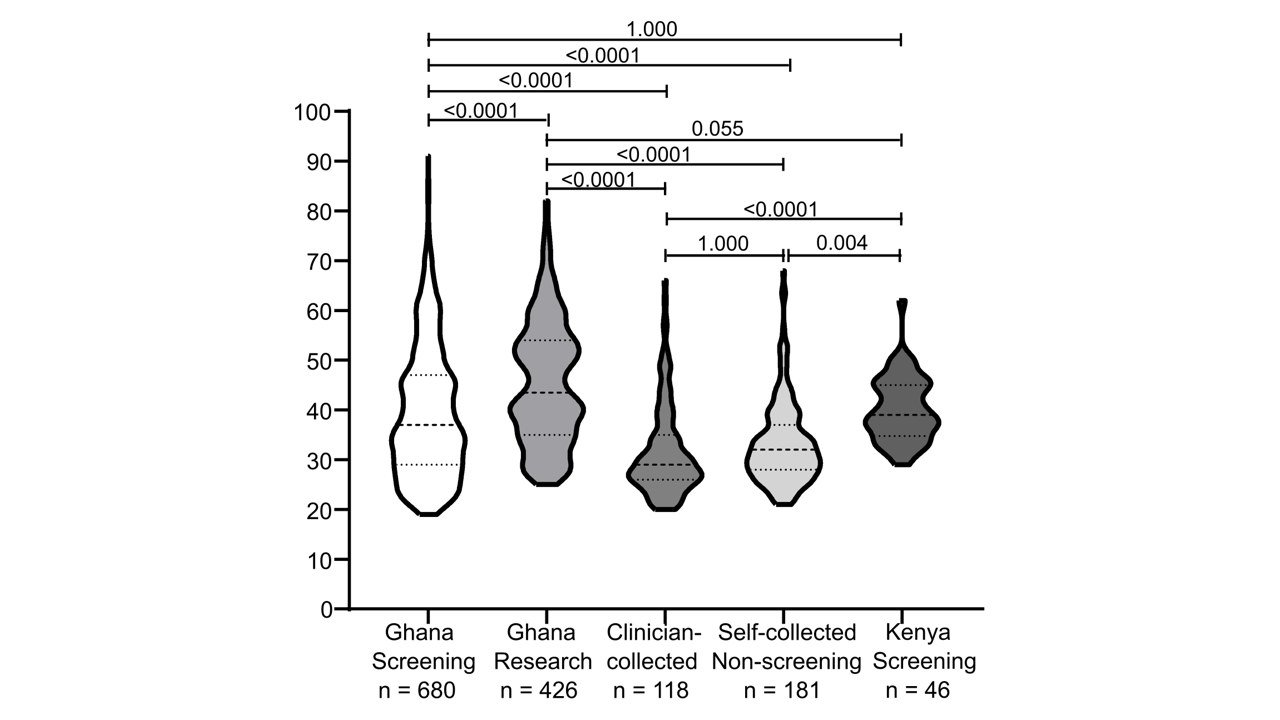
We analyzed HPV genotyping data from cervical samples submitted for diagnostic HPV genotype testing between July 2022 and March 2025. Our database contained results from samples obtained from outreach screening events in Accra, the capital of Ghana (n = 680), a research project in Ghana outside of Accra (n = 426), clinician-collected samples submitted through clinics in Ghana (n = 118), samples from participants in Ghana who independently sought HPV genotyping through community-based providers, pharmacies, clinics, or online testing services outside organized screening programmes (n = 181) and samples from an outreach screening event in Kenya (n = 46). All samples were from women 18 years old and above. Positivity for HPV genotypes (HPV-16, 18, 31, 33, 35, 39, 45, 51, 52, 53, 56, 58, 59, 66, 68) was determined by RT-PCR, using the AmpFire HPV High Risk Genotyping kit.
HPV positivity in the Ghana screening group was 34.9%, with multiple genotypes detected in 39.2% of the positive cases. The main HPV genotype in the Ghana screening group was HPV-39 (19.0%), which was especially prevalent in the younger age group (<30 years), followed by HPV-53 (15.2%) and HPV-68 (15.2%). HPV infection (Odds Ratio (OR) 3.09, Confidence Interval (CI) 1.92–4.97, p < 0.001) and infection with multiple genotypes (OR 3.45, CI 1.42–8.38, p = 0.006) was associated with younger age in the Ghana screening group. In the Ghana research group HPV-53 was the most common genotype (18.9%), followed by HPV-39 (18.0%). In the clinician-collected group HPV-16 (18.6%) was the most common genotype. In the self-collected samples from participants who independently sought HPV testing HPV-39 (17.9%) and HPV-51 (17.9%) were the most common genotypes. In the much smaller Kenya screening group HPV-51 (46.2%) was the most prevalent genotype.
Our study shows HPV genotype distribution in different settings. This emphasizes the importance of systematic population-wide HPV screening to understand local HPV infections patterns.
Introduction
Cervical cancer is the fourth most common cancer in women globally [1]. African women are affected disproportionally, with the highest incidence and mortality rates for cervical cancer reported in Africa [1]. Of the top 20 countries with the highest cervical cancer burden in 2022, 18 are in Africa [2]. In Kenya, cervical cancer is the second most common cancer in women and has the highest mortality rate [3]. In Ghana, cervical cancer is also the second most common cancer in women and ranks third in mortality [3].
Reading this evidence
Use the full paper to check the study design, participant selection, comparator and outcome definitions before drawing a practical conclusion. An association does not by itself show cause and effect. A reported performance measure needs its denominator and uncertainty. A finding from a particular facility, sample or time period should retain that scope when it is discussed elsewhere.
This briefing makes the source accessible within the wider technology & industry desk. It does not assess an individual patient or certify a product. When considering relevance to another health system, examine the original authors’ account of context and limitations, then seek local implementation evidence. The related reporting below provides other studies to read alongside this one; it is a topic connection, rather than a claim that their results are directly comparable.
© 2026 Eliza Mari Kwesi-Maliepaard, Judith A. Osea-Larbi, Celestine K. Nyamari, Yakubu Alhassan, Adelaide K. Sromani, Vera M. Kotey, Stephanie Darko, Randy Tackie, Ruth Kiome, Aisha M. Mohammed, Erica Buadii, Emmanuel K. Quaye, Harry Akligoh, Barikisu A. Ibrahim, Patricia Kaba, Susan Florence Amoako, Esmy Kotey, Seth Agyemang, Joyce M. Ngoi, Lily Paemka, Kwaku Darkwa, Thywill Degley, Nathan Edward Siebu, Charles Ochieng’ Olwal, Collins M. Morang’a, Aida Manu, David Hutchful, Emmanuella Amoako, Frank G. Onyambu, Yaw Bediako. Excerpts reproduced under CC BY. Selection, formatting and contextual notes by Health Signal. The researchers are the authors of the source study, not members of Health Signal’s staff.
Explore connected evidence
- Evidence brief: A collaborative cervical precancer screening strategy with concurrent HPV genotyping and visual inspection using alumni of a training centre across Ghana: The Rotary ‘Protect Your Pearl’ initiative
- Evidence brief: Cervical leukoplakia in Ghana: Unveiling diagnostic challenges and informing low-resource screening strategies
- Evidence brief: Prevalence of high-risk human papillomavirus genotypes and associated factors among HIV-infected women in a reproductive age group attending antiretroviral therapy in Nekemte town, Oromia, Ethiopia