Published in PLOS One on 2026-08-28, this study is presented as an attributed evidence briefing. The excerpts below are the original researchers’ words, reproduced under their Creative Commons Attribution licence. Health Signal has selected the abstract and, where needed, opening background paragraphs; the complete methods, results, limitations and references remain in the linked paper.
Original authors: Tracy N. Phiri, Cherlynn Dumbura, Kuda Mutasa, Deophine Ngosa, Nivea Chuulu, Florence D. Majo, Sandra Rukobo, Claire D. Bourke, Beatrice Amadi, Mutsa Bwakura-Dangarembizi, Adrian R. Martineau, Andrew J. Prendergast, Paul Kelly
Source: PLOS One • DOI 10.1371/journal.pone.0355404
Read the complete primary study ↗ · Creative Commons Attribution licence
From the researchers
Abstract
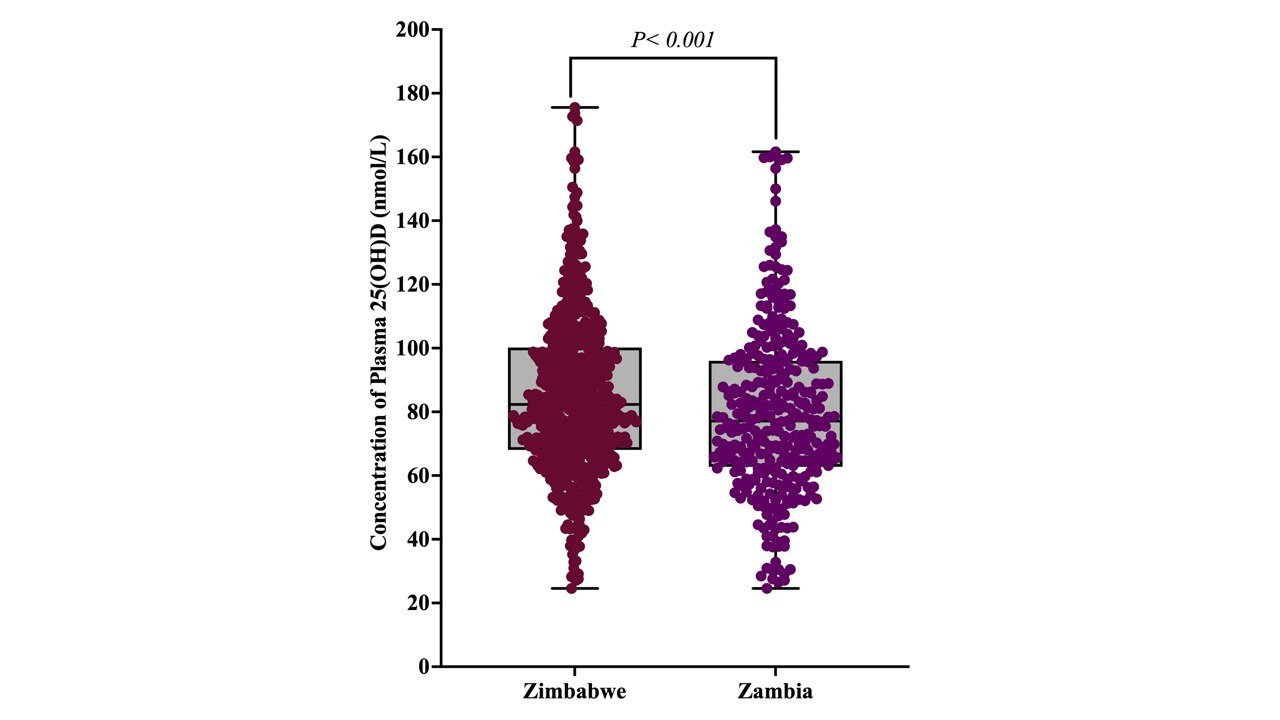
Mortality following severe acute malnutrition (SAM) remains high in Africa. Some children with SAM have altered immune responses and impaired neurodevelopment; however, whether vitamin D deficiency contributes to these poor outcomes remains unclear. We conducted a cross-sectional analysis of circulating 25-hydroxyvitamin D [25(OH)D] concentrations at hospital discharge (25(OH)D) in 442 children aged 0–59 months with SAM at one hospital in Lusaka, Zambia, and two hospitals in Harare, Zimbabwe. Also, we investigated the relationship between 25(OH)D concentrations and host factors. In 442 children, plasma 25(OH)D concentrations were measured using ELISA. Vitamin D deficiency was identified in 33/442 (7.5%; 95% CI: 5.2–10.3) children, all of whom were from Zimbabwe. A multivariable regression model that included age, sex, HIV status, season, oedema, cerebral palsy, and country demonstrated significantly higher 25(OH)D levels among children aged 6–11 months (adjusted (adj) ratio; 1.3; 95% CI: 1.1, 1.6; P = 0.003), 12–23 months (adj ratio; 1.5; 95% CI: 1.3, 1.8; P < 0.001), and 24–59 months (adj ratio; 1.5; 95% CI: 1.3, 1.8; P < 0.001) compared with those <6 months. Sampling during the cool season (adj ratio; 1.2; 95% CI: 1.1, 1.3; P = 0.002), absence of cerebral palsy (adj ratio; 1.2; 95% CI: 1.1, 1.4; P = 0.002) and residence in Zambia (adj ratio; 1.2; 95% CI: 1.1, 1.2; P < 0.001) were associated with higher concentrations of 25(OH)D, even after excluding children <6 months. These findings indicate that vitamin D status among children with SAM is significantly influenced by age, seasonality, cerebral palsy, and geographical location. To facilitate management and improve clinical outcomes in these children, we recommend further investigation into whether the current vitamin D content in ready-to-use therapeutic foods is sufficient for all children and whether additional supplementation improves clinical outcomes, especially in high-risk groups. If deficiency is present, we recommend that children be managed in accordance with local guidelines and policies.
Introduction
Severe Acute Malnutrition (SAM) encompasses two forms of acute malnutrition: severe wasting and nutritional oedema [1]. According to World Health Organisation (WHO) growth standards, SAM in children aged 6–59 months is defined as a mid-upper arm circumference (MUAC) below 115 mm or a weight-for-height z-score (WHZ) below −3 [2], with or without bilateral oedema. Children with SAM who have severe oedema, poor appetite, and/or medical complications such as diarrhoea, pneumonia or metabolic problems need urgent medical intervention and hospitalisation for management [1]. According to the WHO, an estimated 19 million children below the age of 5 years are living with SAM, and 400,000 die each year [3]. A review by Asebe et al. reported that 2.1% (95% CI: 2.0, 2.2%) of children aged between 6 and 59 months in sub-Saharan Africa are affected by severe wasting [4], while in Zambia, the Demographic and Health Survey (DHS) of 2024 reported that approximately 1% of Zambian children are living with SAM [5]. In Zimbabwe, approximately 15,000 children are treated for severe wasting annually [6].
Reading this evidence
Use the full paper to check the study design, participant selection, comparator and outcome definitions before drawing a practical conclusion. An association does not by itself show cause and effect. A reported performance measure needs its denominator and uncertainty. A finding from a particular facility, sample or time period should retain that scope when it is discussed elsewhere.
This briefing makes the source accessible within the wider hospital systems desk. It does not assess an individual patient or certify a product. When considering relevance to another health system, examine the original authors’ account of context and limitations, then seek local implementation evidence. The related reporting below provides other studies to read alongside this one; it is a topic connection, rather than a claim that their results are directly comparable.
© 2026 Tracy N. Phiri, Cherlynn Dumbura, Kuda Mutasa, Deophine Ngosa, Nivea Chuulu, Florence D. Majo, Sandra Rukobo, Claire D. Bourke, Beatrice Amadi, Mutsa Bwakura-Dangarembizi, Adrian R. Martineau, Andrew J. Prendergast, Paul Kelly. Excerpts reproduced under CC BY. Selection, formatting and contextual notes by Health Signal. The researchers are the authors of the source study, not members of Health Signal’s staff.
Explore connected evidence
- Evidence brief: Prevalence and determinants of soil transmitted helminth infections among children on Highly Active Antiretroviral Therapy (HAART) in Mulobezi and Sesheke Districts, Zambia: A cross – sectional study
- Evidence brief: Sex dictates IL-17A regulation: Inflammatory determinants in males versus a potassium-linked metabolic axis in females
- Evidence brief: Time to recovery and its predictors among children aged 6 to 59 months with uncomplicated severe acute malnutrition treated in outpatient therapeutic programs in Adet Woreda, Central Zone of Tigray, Northern Ethiopia: A retrospective cohort study

