Published in PLOS One on 2026-09-25, this study is presented as an attributed evidence briefing. The excerpts below are the original researchers’ words, reproduced under their Creative Commons Attribution licence. Health Signal has selected the abstract and, where needed, opening background paragraphs; the complete methods, results, limitations and references remain in the linked paper.
Original authors: Abdulsalam Ahmed, Hafiz T. A. Khan, Nestor Asiamah
Source: PLOS One • DOI 10.1371/journal.pone.0358944
Read the complete primary study ↗ · Creative Commons Attribution licence
From the researchers
Abstract
Adverse Childhood Experiences (ACEs) are established life-course determinants of adult health, yet evidence linking ACEs to multimorbidity in sub-Saharan Africa remains limited. Nigeria is undergoing rapid demographic and epidemiological transitions characterized by population ageing and a rising burden of non-communicable diseases (NCDs). This study examined whether cumulative ACE exposure predicts multimorbidity among older adults in North-Central Nigeria.
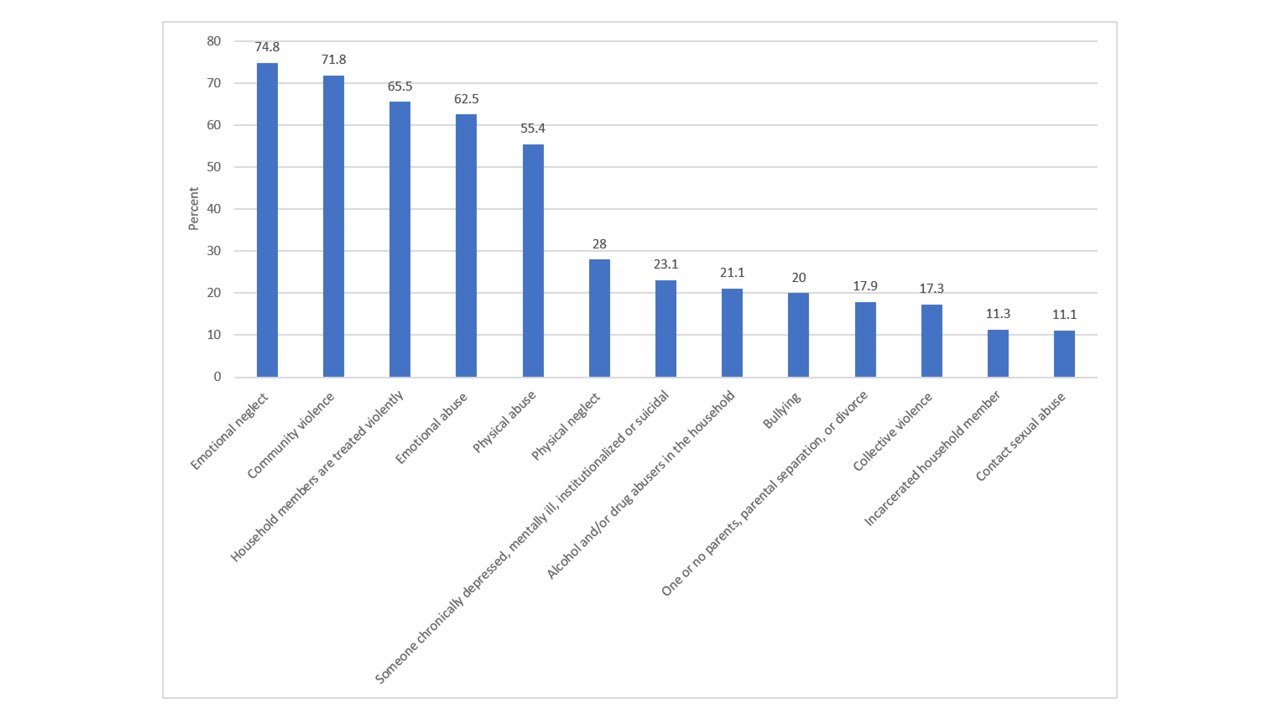
A cross-sectional study was conducted among 734 adults aged ≥60 years in Niger State, Nigeria. ACE exposure before age 18 was assessed using the Adverse Childhood Experiences International Questionnaire (ACE-IQ) across 13 domains. Multimorbidity was defined as the presence of two or more chronic conditions (NICE criteria) from a list of 24 conditions and analyzed both as a count and dichotomized (≥3 vs. < 3 conditions). Descriptive statistics summarized participant characteristics. Chi-square tests examined bivariate associations. Hierarchical logistic regression models estimated adjusted odds ratios (ORs) and 95% confidence intervals (CIs) to determine independent predictors of multimorbidity.
High cumulative ACE exposure was observed, with 68.4% reporting ≥4 ACEs. Multimorbidity was common: 38.4% reported three or more chronic conditions. ACE exposure was strongly associated with multimorbidity (χ² = 116.07, p < 0.001). In unadjusted analysis, participants reporting ≥4 ACEs had significantly higher odds of multimorbidity (OR = 67.14; 95% CI: 9.25–487.04). After adjusting for socio-demographic covariates, cumulative ACE exposure remained an independent predictor (OR = 15.58; 95% CI: 1.33–182.21). Advanced age (≥80 years) and living in three-generation households were also independently associated with multimorbidity.
Cumulative childhood adversity significantly predicts multimorbidity among older Nigerian adults, demonstrating a clear dose–response relationship. These findings underscore the importance of life-course approaches and trauma-informed strategies in public health policy. Early identification and prevention of childhood adversity may contribute to reducing the long-term burden of multimorbidity in low- and middle-income settings.
Background
Adverse Childhood Experiences (ACEs) are increasingly recognized as critical early-life determinants of health across the life course. ACEs refer to potentially traumatic events occurring before the age of 18 years that threaten a child’s physical or psychological well-being. These include child maltreatment (physical, emotional, or sexual abuse) and household dysfunction such as exposure to domestic violence, parental separation, substance misuse, mental illness, or incarceration within the household [1]. Since the landmark ACE Study, evidence has consistently demonstrated a graded relationship between cumulative childhood adversity and adverse health outcomes in adulthood [2]. Recent systematic reviews have reinforced this, showing that individuals with multiple ACEs are at significantly higher risk of chronic diseases in later life [3].
A substantial body of epidemiological research shows that individuals exposed to ACEs are at increased risk of chronic diseases, including hypertension, diabetes mellitus, cardiovascular diseases, and depression [2,3]. ACE exposure is also associated with higher likelihood of engaging in health-risk behaviors—such as tobacco use, harmful alcohol consumption, physical inactivity, and risky sexual behavior—which further elevate the risk of non-communicable diseases (NCDs) and premature mortality [3,5]. Importantly, ACEs frequently co-occur; exposure to one adverse event increases the likelihood of exposure to others, leading to cumulative biological and psychosocial stress [3,4]. Neurobiological evidence suggests that early-life toxic stress can result in long-term dysregulation of neuroendocrine, immune, and metabolic systems, thereby increasing vulnerability to chronic disease across the lifespan [5].
Reading this evidence
Use the full paper to check the study design, participant selection, comparator and outcome definitions before drawing a practical conclusion. An association does not by itself show cause and effect. A reported performance measure needs its denominator and uncertainty. A finding from a particular facility, sample or time period should retain that scope when it is discussed elsewhere.
This briefing makes the source accessible within the wider financing & policy desk. It does not assess an individual patient or certify a product. When considering relevance to another health system, examine the original authors’ account of context and limitations, then seek local implementation evidence. The related reporting below provides other studies to read alongside this one; it is a topic connection, rather than a claim that their results are directly comparable.
© 2026 Abdulsalam Ahmed, Hafiz T. A. Khan, Nestor Asiamah. Excerpts reproduced under CC BY. Selection, formatting and contextual notes by Health Signal. The researchers are the authors of the source study, not members of Health Signal’s staff.
Explore connected evidence
- Evidence brief: Prevalence, spatial patterns and determinants of zero-dose vaccination among children aged 12–23 months in Sub-Saharan Africa: A multilevel spatial analysis
- Evidence brief: Impact of demographic factors and HIV status on Hepatitis B vaccination adherence and completion rate among high-risk populations in Lagos State, Nigeria
- Evidence brief: The association of maternal education with access to maternal care and child mortality in Nigeria: A secondary data regression-based analysis

