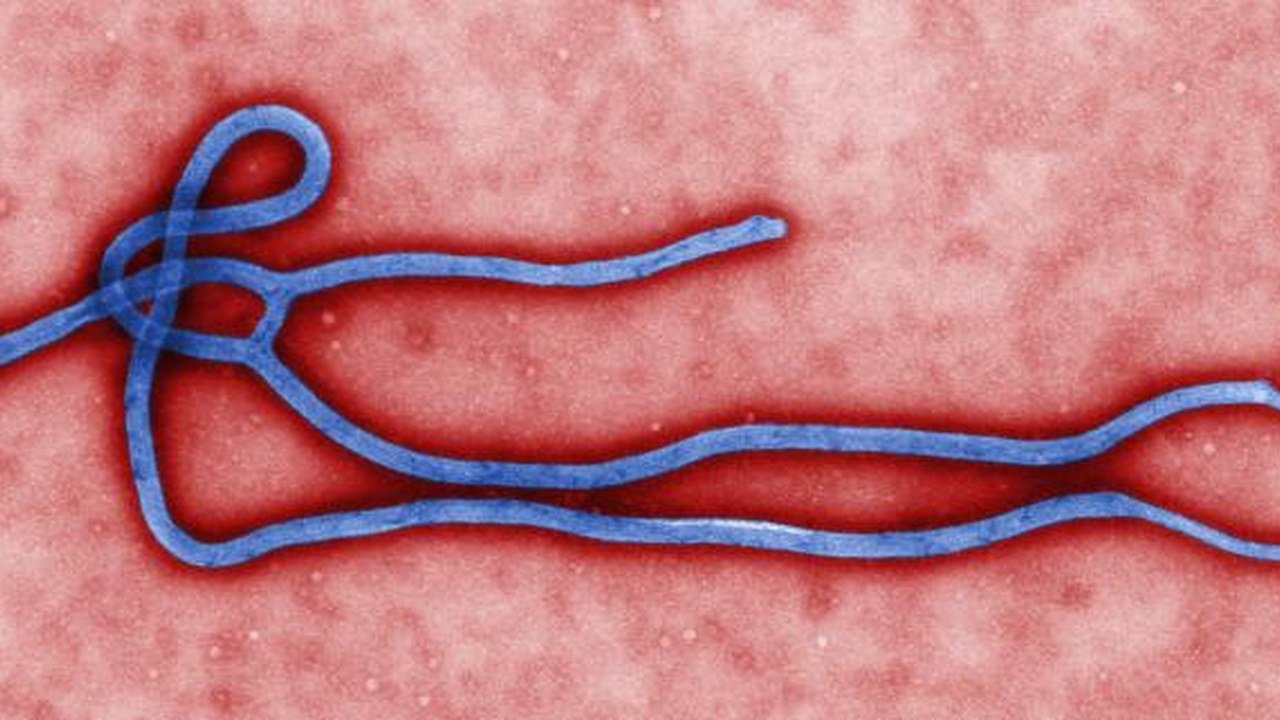
WHO’s African Region reported on 6th October 2026 that Kenya had confirmed its first imported case of Bundibugyo virus disease, a form of Ebola. The patient had been ill in the Democratic Republic of the Congo, travelled through Uganda and arrived in Nairobi on 3rd October. Testing at Kenya’s National Virology Reference Laboratory and KEMRI confirmed the infection. WHO said the patient died on the night of 5th October and was buried the following day under the safe and dignified burial protocol.
At that reporting point, authorities had listed 28 contacts and were tracing 23 passengers and four crew members from the flight. WHO advised against travel or trade restrictions on Kenya, Uganda or the DRC based on the available information. These are dated statements from that report. They must not be presented as today’s final contact totals or as evidence that everybody being followed had become infected.
Why the distinction matters
An imported case establishes that infection was confirmed in a person who arrived from elsewhere. A contact list records people requiring assessment and follow-up. Neither label, on its own, establishes sustained transmission within a community. Reporting should identify the evidence for each stage rather than treating a precautionary response as a case count. A headline can communicate urgency while retaining the geographic and epidemiological scope of the announcement.
The same care applies to the travel history. It explains why the response involves several jurisdictions and transport settings. It does not identify every traveller as a contact with the same degree of exposure, or establish that infection occurred during the journey. The relevant questions concern assessed exposure, the authorities responsible for follow-up and the results of that follow-up. Those answers belong in subsequent dated updates.
What readers should look for next
The useful next record would distinguish new laboratory-confirmed cases from alerts, investigated samples and contacts completing monitoring. It should explain the reporting period, whether a new case has an identified connection to an earlier case and which authority has classified the event. An unchanged tally needs its own date as much as an increasing one. Readers should be able to compare successive reports without mistakenly adding the same people twice.
For hospitals, this development makes the route from recognising a possible exposure to isolation, testing and protected care an important reporting subject. The existence of a plan is only the starting point for assessing that route. Operational evidence could show whether staff know whom to contact, whether the designated referral arrangements are functioning and whether essential protective supplies reach the teams expected to use them.
Keep the archive useful
This article records the 6th October announcement. Later response reports should be linked alongside it, with the newer date visible, rather than silently replacing the original figures. That preserves the sequence of decisions and allows readers to see what changed. Any claim that the event has ended, expanded or changed classification requires a later statement from the responsible public health authorities. The linked sources remain the route to current instructions.
Source-based reporting and analysis by Health Signal Editorial Desk. Read the original source. Evidence reviewed on 12th October 2026; figures retain the date of the cited report.
Connected reporting
Read this alongside Kenya’s Ebola response receives supplies: the next question is where they reach care and WHO updates filovirus surveillance guidance: what health systems should examine.


